
Leriglitazone
- What is Leriglitazone
Leriglitazone (MIN-102) is a novel orally bioavailable, brain penetrating and selective PPAR gamma agonist under development for CNS diseases. It is one of the several metabolites of pioglitazone and has demonstrated sufficient brain penetration and favorable safety profile in humans, allowing PPAR gamma engagement in the CNS above the level that can be safely achieved with pioglitazone and other glitazones.
In clinical trials, it has shown positive cALD outcomes in both paediatric cALD patients in the NEXUS clinical trial and adult AMN patients in the ADVANCE trial. Results from NEXUS demonstrate that paediatric cALD patients are clinically and radiologically stable after over 96 weeks of treatment or at a visit prior to Haematopoietic Stem Cell Transplantation (HSCT). Data from ADVANCE showed that leriglitazone reduced progression of brain lesions (cALD) in AMN patients. More than 170 patients with cALD have received treatment to date and a pivotal study (CALYX) in adult male cALD patients with Gd-positive brain lesions is currently ongoing. The safety and efficacy of leriglitazone in Rett syndrome is currently being assessed in a phase 2 clinical trial (TREE) with read-out by the end of 2026. Leriglitazone has been granted orphan drug status for X-ALD by the FDA and the EMA, as well as Fast Track and Rare Paediatric Disease designation from the FDA for the treatment of X-ALD.
Leriglitazone has been granted marketing authorization approval under exceptional circumstances in the European Union on 21 September 2026 for the treatment of Cerebral Adrenoleukodystrophy (cALD) in males with Adrenoleukodystrophy (ALD) aged 2 to 12 years with non-Gadolinium (Gd) enhancing lesions (i.e. Gd negative) in brain Magnetic Resonance Imaging (MRI), with a Neurological Functional Score (NFS) of 0 or 1.
Leriglitazone showed preclinical proof-of-concept in animal models of multiple other diseases, including AMN, Rett, Friedreich ataxia, MLD and NBIA, by modulating pathways leading to mitochondrial dysfunction, oxidative stress, neuroinflammation, demyelination and axonal degeneration.
1 Best-in-class, selective PPAR gamma agonist Central role in CNS.2 Marketing authorization approval under exceptional circumstances of NEZGLYAL (leriglitazone) in the European Union
3 In the clinic leriglitazone is generally well tolerated without significant safety findings4 Orally bioavailable. Specifically formulated as suspension to achieve high and controlled exposure in patients5 MoA validated in animal models of multiple CNS diseases6 Granted patents in European jurisdictions and US covering multiple CNS indications until 2039
Mechanism of Action in X-ALD
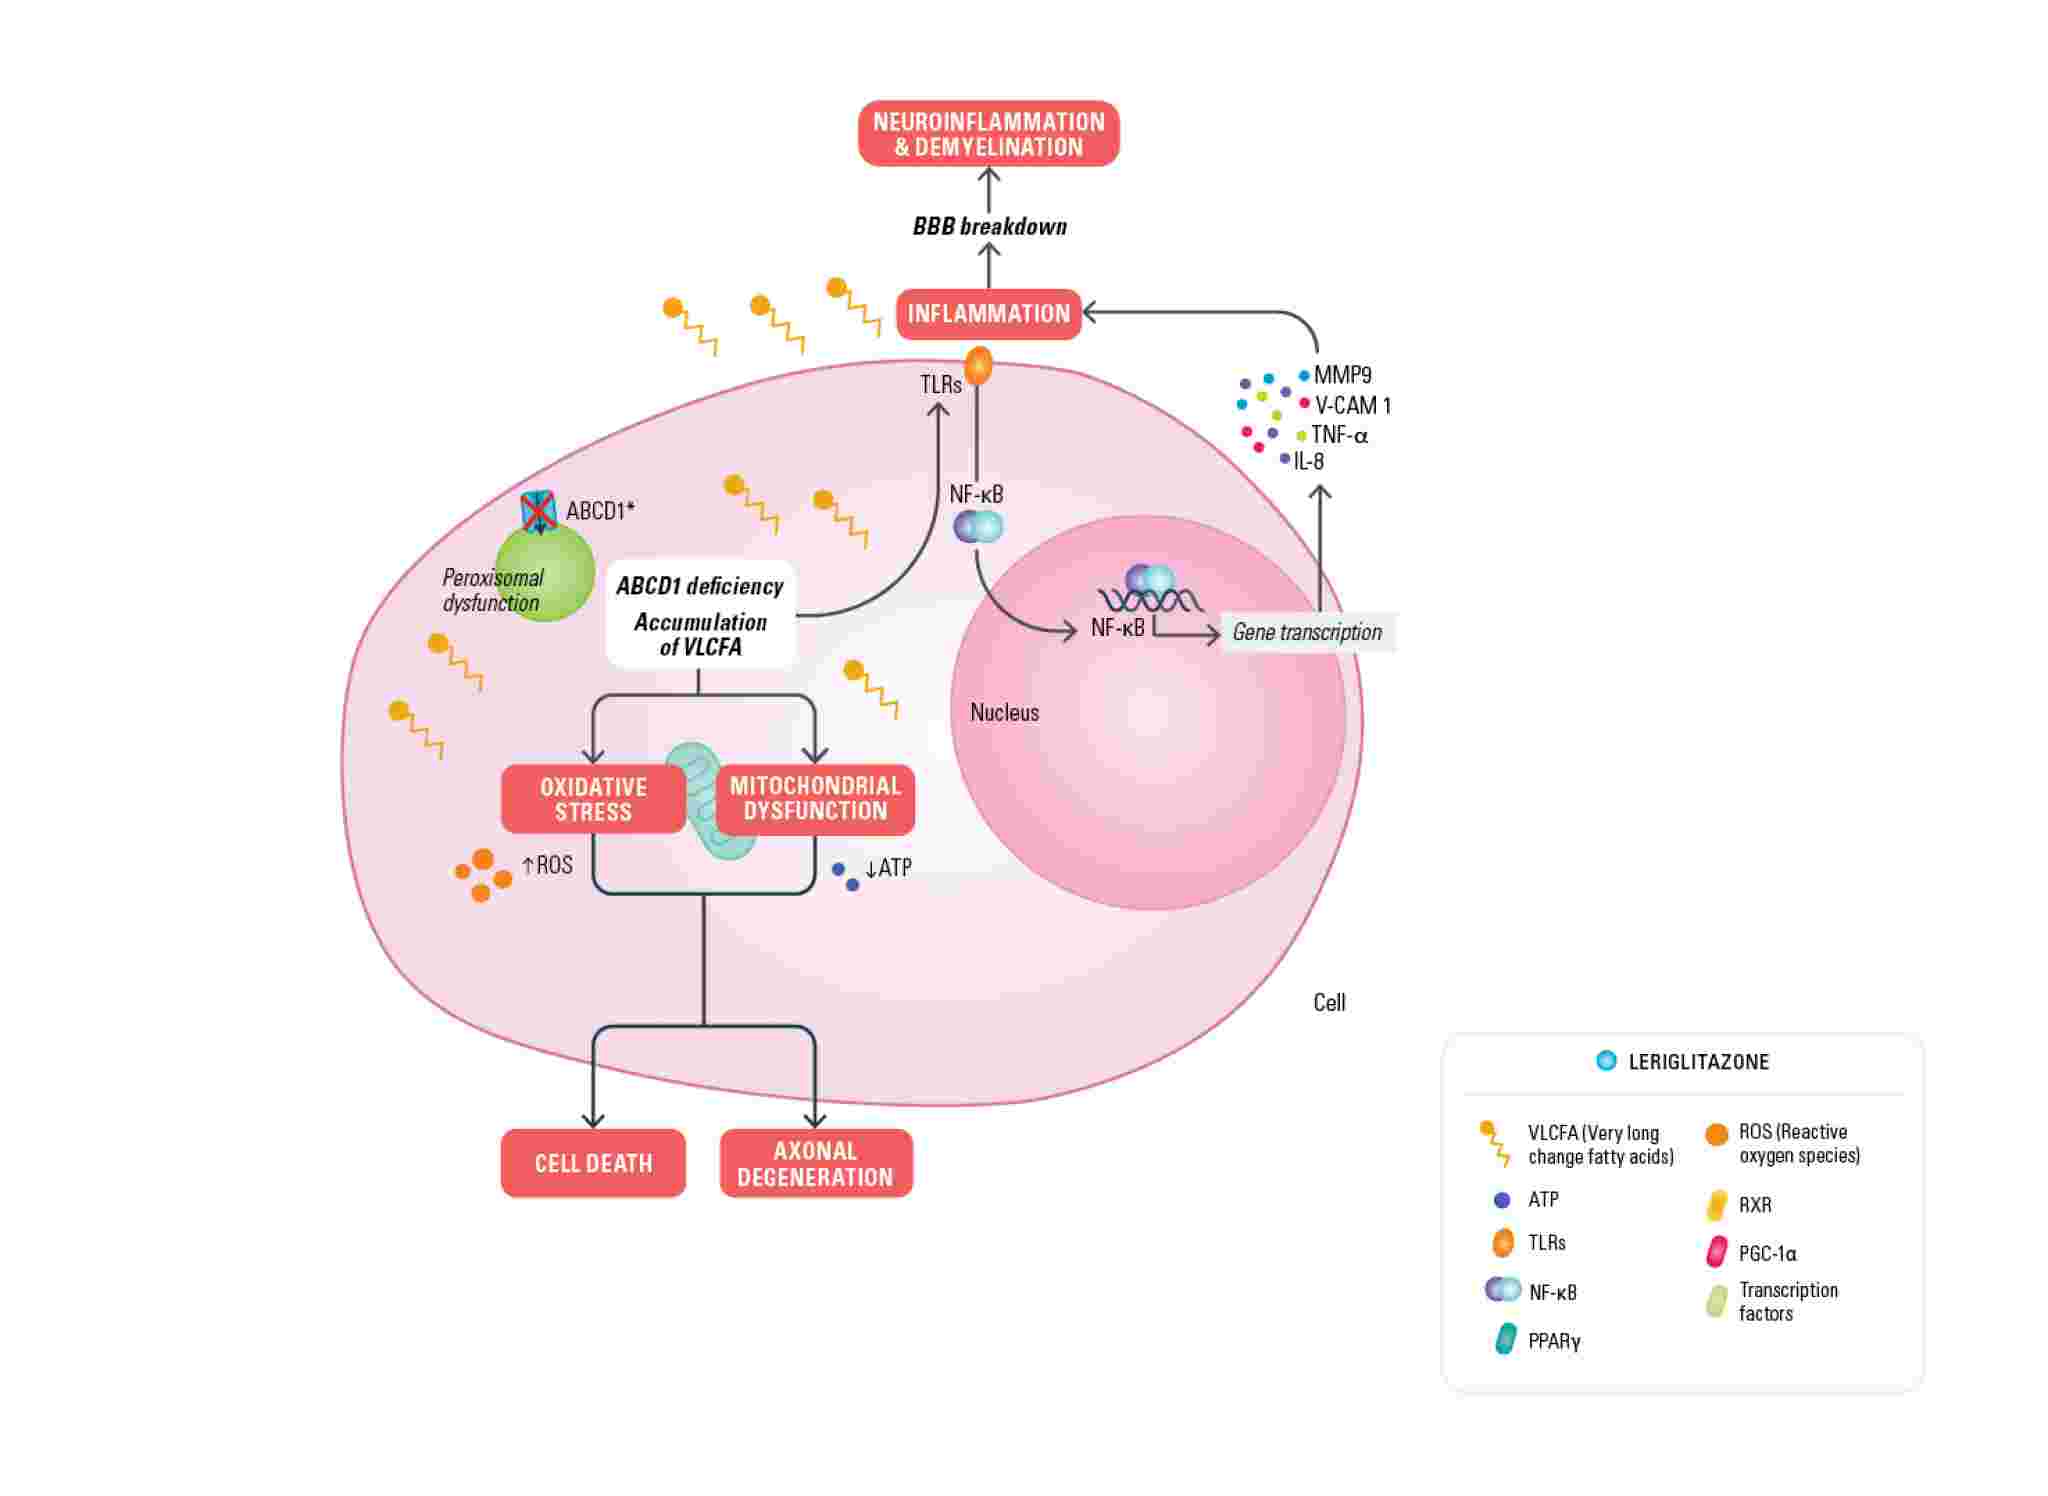
In X-ALD, mutations in the ABCD1 gene located on the X-chromosome cause defective function of the ABCD1 transporter, normally responsible for bringing VLCFAs (very long-chain fatty acids) into the peroxisome. The defective function of the transporter leads to an accumulation of very long-chain fatty acids (VLCFA) in several tissues and a pathogenic cascade of events that contribute to membrane destabilization of the myelin sheath, mitochondrial dysfunction, oxidative stress, neuroinflammation and compromised blood brain barrier (BBB) integrity.
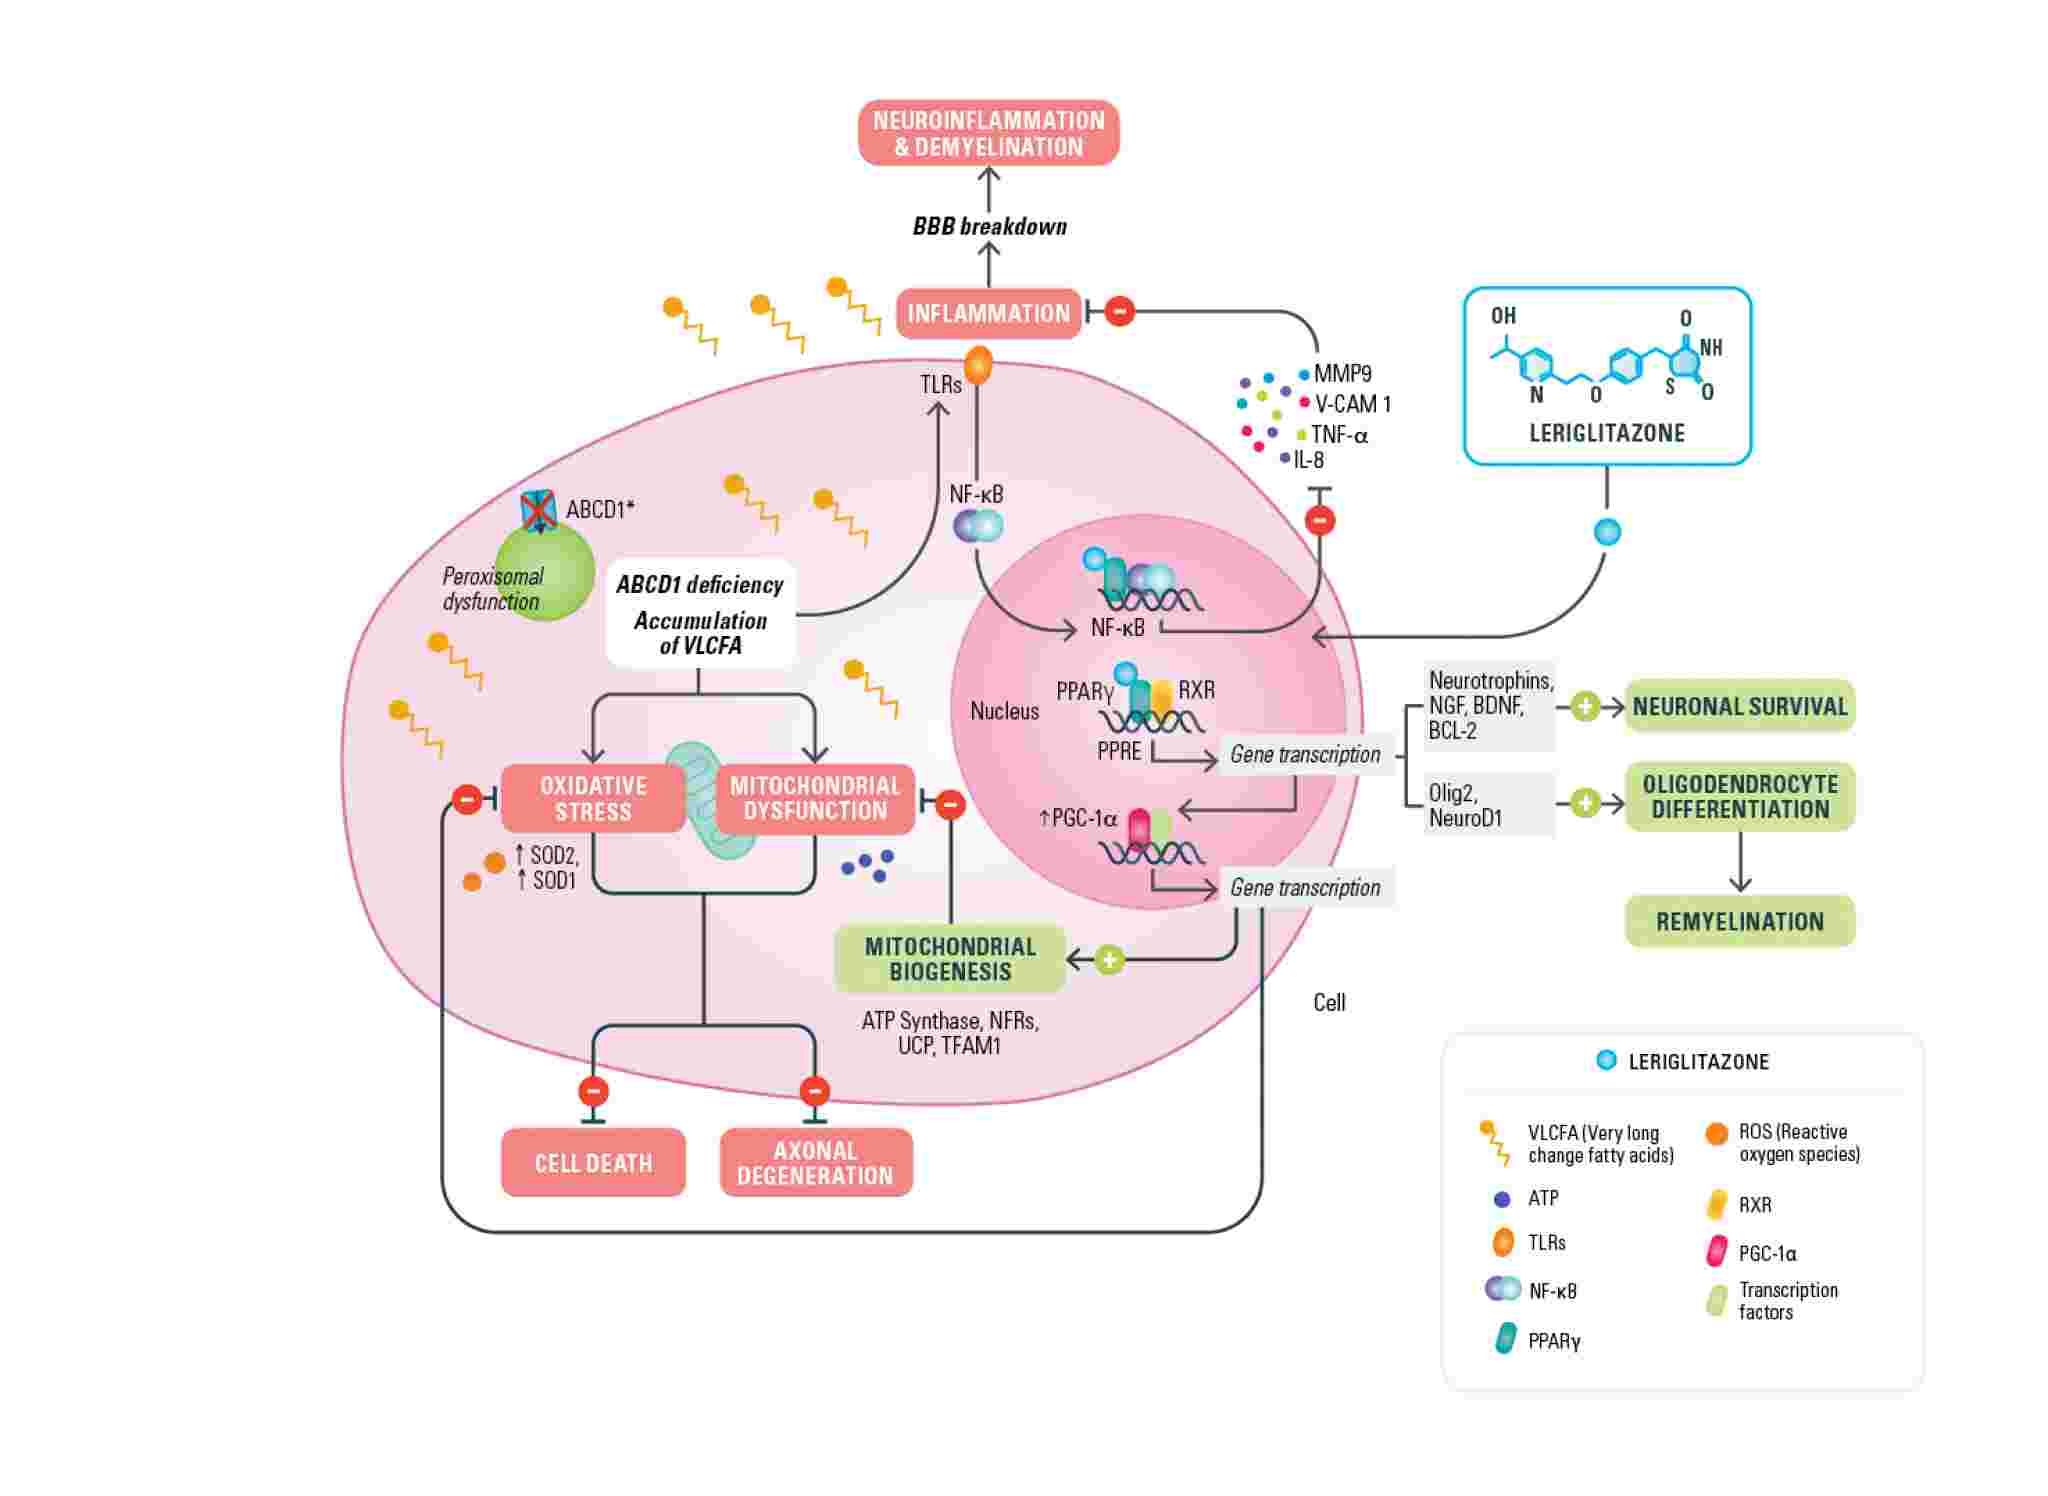
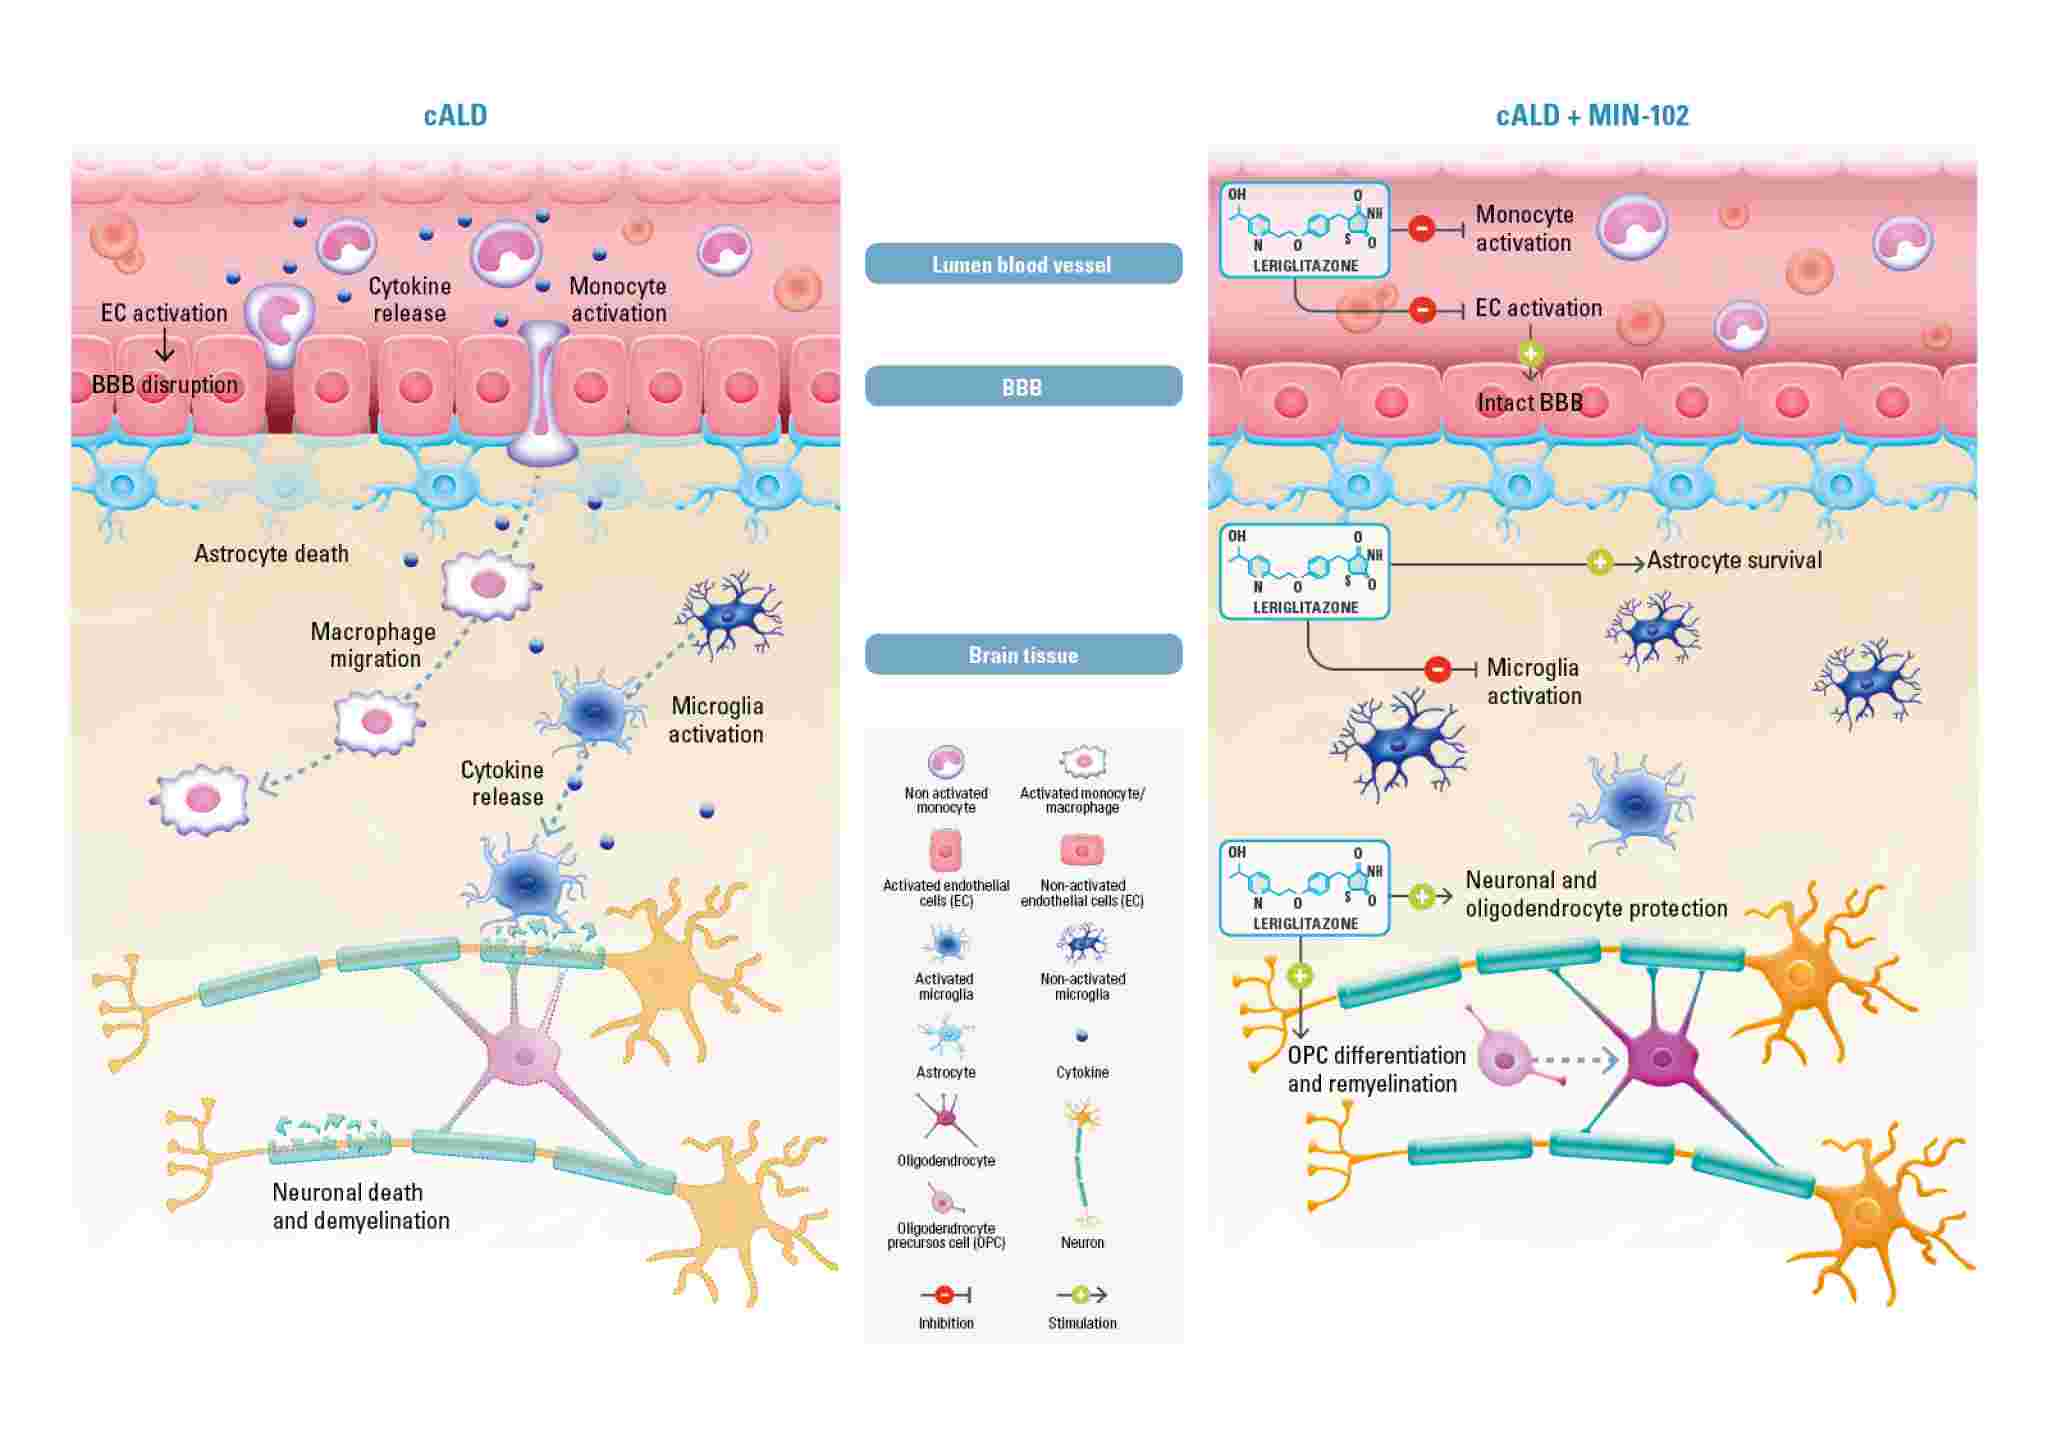
Leriglitazone (MIN-102), by activating PPAR gamma, modulates the expression of genes involved in mitochondrial biogenesis (PGC-1a) and therefore restores the lost energy balance, decreases oxidative stress and restores mitochondrial function caused by the accumulation of VLCFAs. Leriglitazone also increases the expression of genes involved in oligodendrocytes differentiation (olig2, neuroD1) promoting remyelination by oligodendrocyte survival and differentiation and modulates neurotrophin levels resulting in improved neuronal survival. Leriglitazone also interacts with the inflammatory pathway active in X-ALD by decreasing NF-kB levels, reducing macrophage/microglial activation and consequently neuro-inflammation. It also reduces monocyte adhesion to the endothelial cells of the blood brain barrier, a mechanism that leads to BBB disruption and has a prominent role in the initiation of the cALD phenotype. The mechanism of action of leriglitazone in X-ALD was published in Science Translational Medicine Journal.
Mechanism of Action in other CNS diseases
RETT
Rett syndrome is primarily caused by de novo mutations in MECP2 gene on the X chromosome, which affect normal brain development and function. MeCP2 deficiency is associated with alterations in mitochondrial function and structure, reduced energy production, increased oxidative stress and neuroinflammation contributing to impaired neuronal function and maturation.
Leriglitazone, through activation PPAR gamma, improves cellular energy metabolism and mitochondrial function, reduces oxidative stress and neuroinflammation, and ameliorates disease-related features in preclinical models of Rett Syndrome. Preclinical data for leriglitazone in Rett syndrome was published in Journal of Translational Medicine
FRDA
Friedreich's Ataxia is caused by mutations in the FXN gene which result in reduced levels of frataxin, a mitochondrial protein essential for healthy mitochondrial function. Frataxin deficiency leads to mitochondrial dysfunction, impaired energy production, oxidative stress, iron imbalance and progressive damage to nerve and other cells. The maintenance of mitochondrial function is therefore crucial to reduce progression of the disease.
Through the activation of the PPAR gamma/PGC-1 alpha pathway, leriglitazone improves mitochondrial function and iron homeostasis, and reduces oxidative stress. This results in increased neuronal survival, decreased neurite degeneration and improve d motor function in preclinical models of FRDA. Preclinical data for leriglitazone in FRDA was published in the Neurobiology of Disease Journal and in Biomedicine & Pharmacotherapy.
 Privacy Settings